암세포의 항암제 내성에 대해
2020.09.29 · 전영조 전문위원
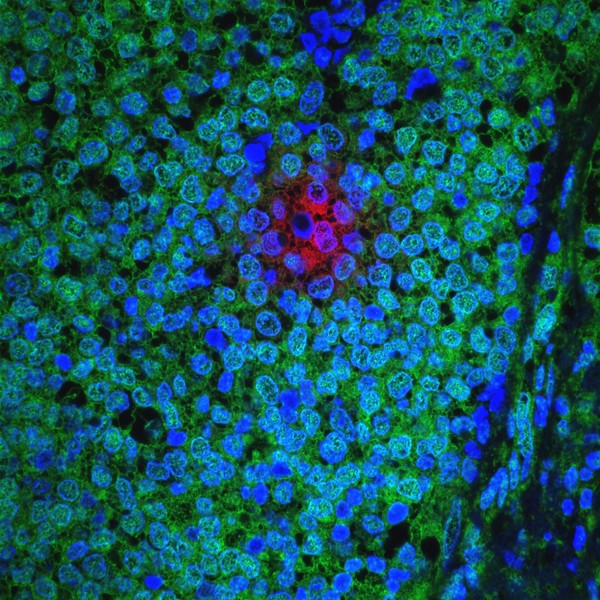
이건 정말 가슴 아픈 이야기고, 너무 자주 일어나는 이야기이다. 암이 진행된 환자는 종양을 수축시키는 데 도움을 주는 약을 받아 가족과 더 많은 시간을 보낼 수 있지만, 몇 주 혹은 몇 달 후에 암이 재발하여 그 약은 더 이상 효과가 없을 수 있다.
약물 내성은 암 치료에 있어서 가장 큰 난제 중 하나로 남아 있다. 내성은 분자 표적치료, 면역치료, 화학요법을 포함한 모든 종류의 암과 모든 치료방법에 걸쳐 존재한다. 암이 치료에 내성이 생기는 이유와 이를 극복하거나 예방하는 방법에 대한 퍼즐을 푸는 것은 국립암연구소가 생물학적 기전(메커니즘)을 이해하는 기초과학과 새로운 치료전략을 실험하는 임상실험 등 여러 측면에서 추진하고 있는 목표다.
암세포 자체와 암세포가 존재하는 국부적 환경(종양 미세 환경)에서 복수의 요인은 약이 얼마나 잘 작용하는가에 기여한다. 이러한 요인은 환자마다 그리고 심지어 동일한 환자의 종양에서도 서로 다를 수 있다. 종양은 유전적, 후생적, 대사적 특성이 다를 수 있는 다양한 세포로 만들어져, 치료에 대한 민감도가 다를 수 있다. 종양은 또한 면역세포와 혈관, 섬유질, 그리고 암세포와 상호작용을 하는 다른 세포와 성분들로 구성되어 있다. 이러한 상호작용은 종종 종양 발생과 진행, 치료에 대한 반응을 촉진한다.
비록 어떤 약이 몇몇 암세포를 죽일 수도 있지만, 거의 항상 그들 중 일부는 저항력을 가지고 치료에서 살아남을 것이다. 암은 종종 생존과 성장을 위한 여러 가지 기전(메커니즘)을 가지고 있는데, 이것은 시간이 지남에 따라 치료에 반응하여 바뀔 수 있다. 작용기전이 다른 치료법을 결합하면 더 많은 암세포를 죽이고 약물 내성이 나타날 가능성을 줄일 수 있는 이유다.
약물 내성에 대한 대부분의 연구는 약의 결합을 손상시키기 위해 단백질을 변형시키는 돌연변이와 같은 유전적 기전(메커니즘)을 확인하는 데 초점을 맞추었다. 연구는 유전자의 활동을 조절하는 후생유전인자와 종양 미세 환경 내 다양한 세포 사이의 역학관계 등 약물 내성의 추가적인 기전(메커니즘)의 중요성을 밝혀내고 있다. 그렇다면 내성을 극복하려면 먼저 이러한 복잡한 생물학적 과정을 이해하고 암 환자 내부에서 펼쳐지는 역동적이고 다차원적인 진화 과정을 더 잘 예측하고 조종할 필요가 있다.
진보된 임상 전 도구와 신약 설계 접근법의 도움을 받아 국립암연구소가 후원하는 연구자들은 암 내성의 보다 명확한 그림을 밝혀내고 이를 극복하기 위한 새로운 치료 접근법을 개발하고 있다.
약물 저항이란?
약물 내성은 암 치료 실패의 주요 원인이다. 치료는 처음에는 효과적일 수 있지만, 암의 이질성과 적응력은 암이 치료에 내성이 생겨 재발하게 할 수 있다. 왜 이런 일이 일어나는지, 어떻게 극복하거나 예방할 것인지에 대한 퍼즐을 푸는 것은 국립암연구소가 생물학적 기전(메커니즘)을 이해하기 위한 기초과학과 새로운 치료전략을 실험하기 위한 임상실험을 포함하여 많은 면에서 추구하고 있는 목표다.
치료 전 : 종양은 분자 특성이 다른 암세포로 이루어져 있어 다른 종류의 치료에 민감하거나 내성이 있을 수 있다.
치료에 대한 반응 : 비록 약물이 일부 암세포를 죽일 수도 있지만, 그들 중 일부는 거의 변함없이 생존한다.
약에 대한 저항력 개발 : 내성이 있는 암세포가 증식해 종양의 재발에 기여할 것이다.
암세포의 가소성의 표적 삼기
2006년부터 의사들은 표피 성장인자 수용체(EGFR) 억제제로 치료한 후 암이 소세포 폐암으로 바뀐 비소세포폐암(NSCLC) 환자의 희귀한 사례에 대해 설명하기 시작했다. 이러한 세포 정체성의 변화는 과학자들이 말하는 세포 가소성의 한 유형이며, 국립암연구소가 후원하는 연구는 그것이 어떻게 암 치료를 방해할 수 있는지에 대한 퍼즐을 맞추고 있다.
세포 소성성은 세포의 외관과 기능(표현형)을 바꾸는 변화를 만들 수 있는 세포의 능력이다. 이러한 변화는 암세포에서 발생할 수 있는 유전적 변화 및 비영양적 변화, 종양 미세 환경 내 다른 세포의 단서 및/또는 약물 치료 때문이다. 세포의 변화 및 적응 능력은 치료에 저항할 수 있는 추가적인 경로를 제공한다.
보다 최근에는 안드로겐 결핍 치료를 받은 전립선암 남성에게서도 비슷한 관찰 결과가 나타났다. 공격적이고 치명적인 형태의 신경내분비 전립선암이 나타났다. 과학자들은 비소세포 폐암과 전립선암 외에도 흑색종과 유방암을 포함한 몇 가지 추가 암 유형에서 세포의 가소성을 설명해왔다.
각기 다른 암들이 세포의 가소성의 패턴을 보여주는 반면, 국립암연구소가 후원하는 연구는 모든 종류의 암에 걸쳐 공통적인 생물학적 기전(메커니즘)을 밝혀냈다. 예를 들어 국립암연구소가 지원하는 연구는 유전자 발현을 조절하는 효소인 EZH2를 비소세포 폐암과 전립선암 모두의 표현형 변화 능력에 포함시켰다. 따라서 한 암에 대한 연구는 다른 암의 내성 패턴에 대한 연구를 풍부하게 하여 여러 종류의 암에 효과가 있을 수 있는 치료법을 식별하는 결과를 가져올 수 있다. 이 사례는 암의 근본적 기전(메커니즘)과 분자적 기전에 대한 우리의 이해가 암이 시작된 곳보다 특정한 유전적 이상을 가진 암을 치료하도록 승인된 약물을 포함하여 정밀 종양학의 발전을 부채질하고 있음을 보여준다.
진화하는 생태계처럼 암을 치료하는 것
종양은 시간이 지남에 따라 진화하는 생태계로 생각할 수 있다. 따라서 연구원들은 암과 치료에 대한 반응을 연구하기 위해 진화 생태학의 개념을 적용하고 있다. 진화생태학은 종들의 상호작용과 종간의 상호작용이 선택과 적응을 통해 종을 형성하는 방법과 그에 따른 진화적 변화의 결과를 연구하는 과학 분야다.
일례로 클리블랜드 클리닉과 케이스 포괄 암센터의 조사원이 이끄는 국립암센터가 후원하는 연구는 최근 비소세포 폐암의 실험모델에서 표적치료에 민감하고 내성이 있는 종양세포 간의 상호작용을 직접 계량화하고 설명하는 '진화형 게임분석'을 개발했다. 그들은 세포간의 상호작용이 다른 조건에서 다르다는 것을 발견했다. 연구원들은 세포들 사이의 상호작용 유형, 즉 "그들이 하는 게임"을 바꾸는 것이 약물 내성 세포가 "승리"하는 것을 방지함으로써 환자에게 도움이 되도록 세포의 진화를 공동으로 선택할 수 있다고 제안한다.
국립암연구소가 후원하는 다른 연구들은 서로 다른 약물 복용량과 일정이 진화적 역학관계의 결과로 약물 내성이 발생할 가능성을 감소시킬 수 있는지 여부를 시험하고 있다. 예를 들어 치료하기 쉬운 민감한 세포의 일부분이 불균형하게 생존할 수 있는 방법으로 약물을 투여할 수 있다면, 그들은 종양 내 내성 세포의 성장을 경쟁하고, 차단할 수 있다. 이러한 적응성 암 치료 접근법으로 종양이 완전히 근절되는 일은 결코 없을 수도 있지만, 비교적 안정된 상태를 유지하여 걷잡을 수 없는 약물 내성의 발달을 제한할 수도 있다.
적응형 암 치료의 효과
국립암연구소가 후원하는 연구는 서로 다른 약물의 복용량과 일정이 암세포 사이의 진화적 역학관계의 결과로 약물 내성이 발생할 가능성을 감소시킬 수 있는지 여부를 시험하고 있다. 적응형 치료에서는 약물에 민감한 세포의 비례가 불균형하게 생존할 수 있도록 하여 약물에 내성이 있는 세포의 성장을 경쟁·차단하는 방식으로 약물을 투여하는데, 이 접근법으로 종양이 결코 퇴치되지 않을 수 있지만, 비교적 안정시켜서 통제할 수 없는 약물의 내성의 발생을 제한할 수 있다.
내성을 피하기 위해 표적을 차단하지 않고 저하시킴
암세포 성장을 견인하는 것과 같은 관심이 가는 단백질을 저하시키기 위해 새로운 기술을 사용하는 것이 새로운 암 치료 전략이다. 이 기술의 한 예는 키메라(PROTAC)를 표적으로 삼는 단백질 분해라고 불리는데, 이것은 원하지 않거나 손상된 단백질을 제거하기 위해 세포의 정상적인 시스템에 의해 분해되도록 특정 단백질에 표시를 하는 분자가 생성된다. 이 접근방식의 장점은 약물의 표적에서 돌연변이나 과잉발현과 같은 일부 암 치료법에서 보이는 약물 내성의 메커니즘을 피할 수 있다는 것이다.
예를 들어, 예일대학교의 국립암연구소가 자금을 지원한 연구원들은 전립선암에 대한 잠재적 치료법으로 PROTAC 분자를 만들었다. 안드로겐 수용체(AR) 신호는 전립선암 시작과 성장에 중추적인 역할을 하며, 안드로겐 수용체를 억제하는 약물은 전이성 질환 환자의 치료 기준이다. 불행히도 안드로겐 수용체 억제제로 치료된 대부분의 종양은 결국 약물 내성을 갖게 된다. 저항의 어떤 기전은 이러한 약물이 존재함에도 불구하고 지속적인 안드로겐 수용체 신호를 보내게 된다.
예일 팀이 발명한 PROTAC 분자는 안드로겐 수용체 표적삼기 부분과 E3 리가아제라고 불리는 단백질에 선택적으로 결합하는 부분으로 구성된다. E3 리가제는 단백질을 분해하는 세포의 정상적인 시스템의 일부분이다. 미국 코네티컷 주 뉴 헤이븐의 아르비나스 주식회사는 국립암연구소의 중소기업혁신연구(SBIR) 프로그램의 추가 지원을 받아 안드로겐 수용체 치료 후 암이 진행된 전이성 전립선암 환자를 대상으로 한 임상시험에서 이 PROTAC를 추가 개발, 시험하고 있다.
국립암연구소의 자금후원의 도움으로 PROTAC와 다른 유사한 기술은 약 이브루티닙(상표명 : 임브로비카)에 내성이 생긴 만성 림프구 백혈병을 포함한 다른 암 유형의 내성을 다루는 데 있어 가능성을 보여주었다.
PROTACS가 암-유발 단백질을 죽이기 위해 우리 세포의 자연 폐기 시스템을 사용하는 방법
국립암연구소가 지원하는 새로운 암 치료 전략은 암세포의 성장을 촉진하는 단백질을 저하시키기 위해 새로운 기술을 사용한다. 세포의 정상적인 기전(메카니즘)에 의한 변질을 위해 특정 단백질에 딱지를 붙이는 분자를 생성시키는 키메라(PROTAC) 기술을 예로 들 수 있다.
우리 세포가 정상적으로 하는 것
인간 세포는 단백질이 잘못 접히거나 더 이상 필요하지 않을 때 단백질을 처리하는 메커니즘을 가지고 있다.
1. E3 ubiquitin ligases는 세포 안의 쓰레기 경찰처럼 행동하는 분자로, 항상 움직이는 단백질을 찾는다.
2. 리가제는 유비퀴틴 분자를 가진 단백질에 '쓰레기 경찰에서 붙인 표'라는 딱지를 붙여 폐기한다.
3. 단백질이 충분한 딱지, 즉 꼬리표를 충분히 받으면, 단백질은 프로테아솜으로 향하게 되는데, 프로테아솜은 표시된 단백질을 주워 폐기하는 세포의 '쓰레기 트럭'과 같은 작용을 한다.
어떤 비정상적인 단백질은 암을 유발한다.
비정상적인 단백질은 세포 성장의 통제 불가로 인하여 암을 유발할 수 있다.
PROTAC는 암을 유발하는 단백질을 분해시키기 위해 이 정상적인 과정을 이용한다.
1. 한쪽 끝은 특별히 암-유발 단백질과 결합한다.
2. PTOTAC 분자의 반대쪽 끝은 E3 리가아제(쓰레기 경찰)와 결합하여 암을 유발하는 단백질을 딱지를 붙이거나 티켓을 발급한다.
3. PROTAC 분자는 암을 유발하는 단백질을 단백질(쓰레기 트럭)에 전달하여 폐기할 수 있도록 이미 존재하는 정상적인 과정을 이용한다.
진행성 임상 전 모델을 사용하여 내성 해결
연구원들은 전통적으로 암 세포 주를 이용하여 암세포를 치료법에 민감하게 하거나 내성을 갖게 하는 돌연변이와 다른 기전을 연구해 왔다. 그러나 세포주가 항상 환자들에게서 발견되는 암의 주요 특징을 공유하는 것은 아니다. 또 암 세포 주는 사람에게서 발견되는 종양의 3차원 구조와 종양 미세 환경 내 주변 세포와의 관계가 부족하다.
환자의 암 표본에서 이식시킨 종양의 숙주 역할을 하는 쥐와 같은 동물 모델은 인간에게서 발견되는 종양과 더 밀접하게 유사할 수 있다. 동물모델의 종양 미세 환경과 암의 성장, 진행, 치료 효과는 사람에게서 발견되는 것과 더 밀접하게 유사하다. 그러나 동물 모델은 비싸고, 생산하는데 수개월이 걸릴 수 있으며, 한 번에 몇 개 이상의 약물을 시험하기 위해 충분히 대량으로 만들어지지 않는다. 그들은 또한 온전한 면역 체계가 부족하여 면역 체계와 암 사이의 상호작용을 연구하기에 불충분하다. 현재의 암 모델은 일부 연구 질문에 대답하는 데 유용하지만, 추가적인 도구가 필요하다.
국립암연구소가 후원하는 연구자들은 새로운 기술과 모델을 활용하여 약물 내성에 대한 보다 완전한 이해를 얻고 있다.
게시 : 2020년 8월 31일
Cancer Drug Resistance: Unraveling Its Complexity
Posted: August 31, 2020
On This Page
• Targeting Cancer Cell Plasticity
• Treating Cancers Like Evolving Ecosystems
• Degrading—Not Blocking—the Target to Avoid Resistance
• Using Advanced Preclinical Models to Address Resistance
It’s a heartbreaking story, and one that happens too often. A patient with advanced cancer receives a drug that helps shrink their tumors, allowing them more time with family, but then weeks or months later the cancer comes back and the drug no longer works.
Drug resistance remains one of the biggest challenges in cancer therapy. It exists across all types of cancer and all modes of treatment, including molecularly targeted therapy, immunotherapy, and chemotherapy. Solving the puzzle of why cancers become resistant to therapy and how to overcome or prevent it is a goal that NCI is pursuing on many fronts, including basic science to understand biological mechanisms and clinical trials testing new treatment strategies.
Multiple factors, within cancer cells themselves and in the local environment in which the cancer cells exist (the tumor microenvironment), contribute to how well a drug works. These factors may differ from patient to patient and even among tumors in a single patient. Tumors are made of diverse cells that may have different genetic, epigenetic, and metabolic characteristics that have different sensitivities to treatment. Tumors also consist of immune cells, blood vessels, fibroblasts, and other cells and components that interact with the cancer cells. These interactions often promote tumor development, progression, and response to treatment.
Although a drug may kill some cancer cells, almost invariably a subset of them will be resistant and survive the treatment. Cancers often have multiple mechanisms for surviving and growing, which may change over time and in response to treatment. That is why combining treatments that have different mechanisms of action can kill more cancer cells and reduce the chance that drug resistance will emerge.
Most of the research on drug resistance has focused on identifying genetic mechanisms, such as mutations that alter a protein such that it impairs the binding of a drug. Research is revealing the importance of additional mechanisms of drug resistance, such as epigenetic factors that regulate the activity of genes and the dynamics between diverse cells in the tumor microenvironment. Overcoming resistance, then, requires understanding these complex biological processes in the first place, to better anticipate and steer the dynamic, multidimensional evolutionary process unfolding inside a patient with cancer.
Aided by advanced preclinical tools and new drug design approaches, NCI-funded researchers are revealing a clearer picture of cancer drug resistance and developing new treatment approaches to overcome it.
What is Drug Resistance?
Drug resistance is a major cause of cancer treatment failure. While a treatment may be effective iniyially, the heterogeneity of cancer and its ability to adapt can allow the cancer resistant to the treatment and regrow. Solving the puzzle of why this happens and how to overcome or prevent it is a goal that NCI is pursuing on many front, including basic science to understand biological mechanisms and clinical trials testing new treatment strategies.
Before Treatment : Tumors consist of cancer cells with different molecular features, which may make them sensitive or resistant to different types of treatment.
Responding to treatment : Although, a drug may kill some cancer cells(the sensitive cells), a subset of them almost invariably survives(the resistant cells)
Developing Drug Resistnace : The cancer cells that are resistant will multiply, contributing to the regrowth of the tumor.
Targeting Cancer Cell Plasticity
Starting in 2006, doctors began to describe rare cases of patients with non-small cell lung cancer (NSCLC) whose cancers transformed into small cell lung cancer after treatment with EGFR inhibitors. This change in cell identity is one type of what scientists refer to as cell plasticity, and NCI-funded research is piecing together the puzzle of how it may hinder cancer treatment.
Cell plasticity is a cell’s ability to undergo changes that alter its appearance and function (its phenotype). These changes can occur in cancer cells because of genetic and nongenetic alterations, cues from other cells in the tumor microenvironment, and/or drug treatment. A cell’s ability to change and adapt offers it additional routes to resist treatment.
More recently, similar observations emerged from men with prostate cancer who were treated with androgen deprivation therapy: aggressive and deadly forms of neuroendocrine prostate cancers emerged. In addition to NSCLC and prostate cancer, scientists have described cell plasticity in several additional cancer types, including melanoma and breast cancer.
While different cancers demonstrate their own patterns of cell plasticity, NCI-funded research has revealed some biological mechanisms that are common across cancer types. For example, research supported by NCI has implicated EZH2, an enzyme that regulates gene expression, in the ability of both NSCLC and prostate cancer to change phenotypes. Thus, research on one cancer may enrich studies of resistance patterns in other cancers, resulting in the identification of treatments that could work for several cancer types. This example illustrates that our understanding of the fundamental and molecular mechanisms of cancer is fueling advances in precision oncology, including drugs approved to treat cancers with specific genetic abnormalities rather than where in the body the cancer started.
Treating Cancers Like Evolving Ecosystems
A tumor can be thought of as an ecological system that evolves over time. Researchers are therefore applying the concepts of evolutionary ecology to study cancer and its response to treatment. Evolutionary ecology is a scientific field that examines how interactions among species and between species and their environment shape species through selection and adaptation, and the consequences of the resulting evolutionary change.
As an example, NCI-funded research led by investigators at Cleveland Clinic and Case Comprehensive Cancer Center recently developed an "evolutionary game assay" that directly quantifies and describes the interactions between tumor cells that are sensitive and resistant to a targeted therapy in an experimental model of NSCLC. They found that the interactions between cells were different under different conditions. The researchers suggest that changing the types of interactions between cells—in other words, the "games they play"—can co-opt the cells’ evolution to better help the patient by preventing drug-resistant cells from “winning.”
Other NCI-funded studies are testing whether different drug doses and schedules might decrease the likelihood that drug resistance will develop as a result of evolutionary dynamics. For example, if drugs can be given in a way that allows a proportion of the easier-to-treat sensitive cells to disproportionately survive, they may compete with and block the growth of the resistant cells in the tumor. With this adaptive cancer therapy approach, it is possible that the tumor may never be completely eradicated, but it may remain relatively stable, thereby limiting the development of uncontrollable drug resistance.
How Adaptive Cancer Therapy Works
nci-funded studies are testing whether different drug doses and schedules might decrease the likelihood that drug resistance will develop as a result of evolutionary dynamics between cancer cells. In adaptive therapy, drugs are given in a way that allows a proportion of the drug-sensitive cells to disproportionately survive, so that they compete with and block the growth of drug-resistant cells, With this approach, it is possible that the tumor may never be completelt eradicated, but it may remain relatively stable, thereby limiting the development of uncontrollable drug resistance.
Degrading—Not Blocking—the Target to Avoid Resistance
Using new technology to degrade proteins of interest, such as those that drive cancer cell growth, is an emerging cancer treatment strategy. One example of this technology is called proteolysis targeting chimera (PROTAC), in which molecules are generated that tag a specific protein for degradation by a cell’s normal machinery for getting rid of unwanted or damaged proteins. An advantage of this approach is that it can avoid some mechanisms of drug resistance seen with some cancer therapies, such as mutations in the target of a drug or overexpression of the target.
For example, NCI-funded researchers at Yale University created a PROTAC molecule as a potential treatment for advanced prostate cancer. Androgen receptor (AR) signaling plays a pivotal role in prostate cancer initiation and growth, and drugs that inhibit ARs are the standard of care for patients with metastatic disease. Unfortunately, most tumors treated with AR inhibitors eventually develop drug resistance. Some mechanisms of resistance result in continued AR signaling despite the presence of these drugs.
The PROTAC molecule the Yale team invented consists of an AR-targeting portion and a portion that binds selectively to a protein, called E3 ligase. The E3 ligase is part of the cell’s normal machinery that degrades proteins. With additional support from NCI’s Small Business Innovation Research (SBIR) program, Arvinas, Inc. of New Haven, Connecticut, is further developing and testing this PROTAC in clinical trials for patients with metastatic prostate cancer whose cancer has progressed after AR therapy.
With the help of NCI funding, PROTAC and other similar technologies have shown promise in addressing resistance in other cancer types, including chronic lymphocytic leukemia that has become resistant to the drug ibrutinib (Imbruvica).
HOW PROTACS USE OUR CELLS’ NATURAL DISPOSAL SYSTEM TO KILL CANCER-CAUSINF PROTEINS
An emerging cancer treatment strategy supported by NCI uses new technology to degrade proteins that drive cancer cells growth. One example is proteolysis targeting chimera(PROTAC) technology, in which molecules are generated that tag a specific protein for degredation by a cell’s normal machinery.
What our cell do normally
Human cells have a mechanism to dispose of proteins when they become mis-folded, or are no longer needed.
ubiquitin ligases are molecules that act like the garbage police in a cell, always looking for proteins that need to g
ligases tag proteins with a ubiquitin molecules, labeling the proteins for destruction. ‘a ticket from the garbage police’
the protein gets enough tickets, or a chain of tags, the protein is directed to the proteasome, which acts like ‘the garbage truck’ of the cell that picks up and disposes the the marked proteins.
Some abnormal proteins cause cancer
abnormal proteins can contribute to the uncontrolled growth of cells, leading to cancer.
PROTAC harnesses this normal process to degrade cancer-causing proteins
end binds specifically with a cancer-causinf protein.
other end of the PTOTAC molecule binds with the E3 ligase( garbage police) and starts tagging, or issuing tickeds to, cancer-causing protein.
PROTAC molecule takes advantage of a normal process that already exists to direct the cancer-causing protein to the proteasome(garbage truck) for disposal.
Using Advanced Preclinical Models to Address Resistance
Researchers have traditionally used cancer cell lines to study mutations and other mechanisms that make cancer cells sensitive or resistant to therapies. But cell lines do not always share key features of cancers found in patients. In addition, cancer cell lines lack the three-dimensional structure of a tumor found in a person and the relationships with surrounding cells in the tumor microenvironment.
Animal models, such as mice that carry tumors implanted from a sample of a patient’s cancer, can more closely resemble the tumors found in humans. The tumor microenvironment and cancer growth, progression, and treatment effects of animal models more closely mimic those found in people. However, animal models are expensive, can take months to produce, and are not made in large enough quantities for testing more than a few drugs at a time. They also lack an intact immune system, making them inadequate to study the interaction between the immune system and cancer. While current cancer models are useful for answering some research questions, additional tools are needed.
NCI-funded researchers are leveraging new technologies and models to gain a fuller understanding of drug resistance. They include three-dimensional human tumor cultures and engineered platforms that support living human tissues, both of which incorporate cells that surround and interact with tumor cells in the tumor microenvironment to mimic conditions in the human body.
Miniature tumors called patient-derived tumor organoids are three-dimensional cancer cell clusters grown in the lab from a sample of a patient’s tumor. Scientists are using them in the laboratory to study various aspects of cancer biology, including mechanisms of drug resistance. Researchers have developed organoids from a variety of cancer types, including breast, prostate, liver, brain, and pancreatic cancer.
One example of this research is in pancreatic cancer, which is one of the most lethal cancer types, in part because it is largely resistant to treatment and is generally detected at a late stage after the cancer has spread. NCI-funded researchers at Cold Spring Harbor Laboratory in New York and their collaborators have created a “living library” of pancreatic cancer organoids derived from patient samples from multiple clinical institutions. In a retrospective analysis of a small number of patients, the organoid’s sensitivity to chemotherapy reflected the patient’s response to therapy. In addition, tumor sampling in a single patient over time predicted the development of chemotherapy resistance that paralleled disease progression in the patient. Understanding why resistance emerges and having models to help predict it could improve the selection of treatments for patients in the future.
Scientists are developing additional cancer models that accurately represent the structure and function of tumors in human organs and tissues. For example, tissue chips are three-dimensional cross sections of living human tissue on a device about the size of a computer memory stick. For cancer researchers, tissue chips and other engineered tumor systems are enhancing the understanding of tumor physiology and aiding cancer treatment research.
For example, NCI is funding research projects that are developing and using engineered tumor systems to study drug response and resistance in cancers of the brain, ovaries, and breast. In addition, NCI’s SBIR program has supported several companies developing cancer chips, including one developed by researchers at the University of Virginia and HemoShear Therapeutics, LLC of Charlottesville, Virginia, to assess drug sensitivity and resistance in pancreatic cancer.
암스쿨에 게재된 기사는 미국국립암연구소(NCI), 미국암협회(ACS), 국립암센터(NCC), 일본국립암연구소(NCCJ), 엠디앤더슨암센터(MD Anderson Cancer Center) 등 검증된 기관의 검증된 자료를 토대로 작성되었습니다.
이 글은 2020년 9월 작성 시점의 정보입니다. 치료 기준·급여 정보는 바뀌었을 수 있으니, 진료와 치료 결정은 반드시 담당 의료진과 상의하세요.



