국립암연구소는 CAR T-세포요법 임상시험의 활성화를 위해 노력한다
2020.05.08 · 전영조 전문위원
국립암연구소는 CAR T-세포요법 임상시험의 활성화를 위해 노력한다
2010년에 국립암연구소 연구팀이 CAR T-세포요법이라는 새로운 형태의 암 치료법에 대한 첫 번째 연구를 발표했는데, 병명이 진행성 림프종 환자 한 명에 대해 보고하면서 연구원들은 치료 후 "극적인 퇴행"이라고 말했다. 다음 해, 펜실베이니아 대학의 연구원들은 CAR T-세포요법을 사용하여 진행성 백혈병 환자를 치료한 유사한 결과를 보고했다.
7년 동안에 식품의약국(FDA)은 최초의 2가지 CAR T세포 치료제를 승인했고, 올해 중에 세 번째 승인을 앞두고 전 세계 연구단체들이 새로운 CAR T세포 치료제를 빠르게 개발하고 있다.
이러한 암 치료법들은 소수의 다른 암 치료법들과 마찬가지로 대중의 관심을 끌었고, 연구자들의 상상력을 사로잡았다. 부분적으로, 그것은 그들이 몇몇의 혈액 암에 걸린 사람들에게서 암을 제거할 수 있는 놀라운 방법이기 때문이다. 그것은 또한 암이 어디서 유래되었는지, 즉 환자 자신의 혈액 때문이다. 그래서 그 혈액의 성분이 치료제를 만드는 데 사용된다.
이러한 구성 요소를 환자에게 되돌려주는 치료제로 전환하려면 매우 복잡한 제조 과정이 필요하다. 이것이 CAR T-세포 요법이 다른 대부분의 암 치료와 차별화되는 점의 일부라고 국립암연구소의 암 치료 및 진단 부서(DCTD)의 프로젝트 담당자인 앤서니 웰치 박사는 설명했다.
웰치 박사는 "CAR T 세포의 경우, 그 과정이 제품"이라고 말했다. 그 과정 또한 비용이 많이 들고 복잡하며 규제가 심하다. 그것은 이러한 개별화된 CAR T세포요법을 시행하는 것이 대량으로 제조되는 '기성품' 약물의 치료법보다 더 제조하기 힘든 것으로 만드는 것은 인간을 임상시험 하는 검사이기 때문이다. CAR T 세포를 만들 수 있는 능력을 가진 실험실과 센터는 거의 없으며, 이는 CAR T 세포를 더 광범위하게 테스트할 수 있는 능력을 제한하기 때문이다.
이런 어려움에 대응하기 위해, 국립암연구소의 암 치료 및 진단부와 국립암연구소의 지도부는 1년여 전에 프레데릭 국립암연구실험실(FNLCR)의 전문가들에게 암 치료용 CAR T 세포와 같은 세포 치료법을 개발하는 일을 맡겼다. 구체적으로는 복수의 병원 현장에서 실시되는 임상시험에서 이러한 치료법의 시험 능력을 가속화하는 것이 목표였다.
이러한 노력의 지원을 받는 초기 임상시험은 급성 골수성 백혈병(AML)이 진행된 어린이와 청소년들에게서 CD33이라는 암세포의 단백질을 표적으로 설계된 CAR T세포요법을 시험하는 첫 번째 시험이 될 것이다. 이 임상시험은 궁극적으로 메릴랜드 주 베데스다의 국립보건원 임상 센터와 필라델피아 어린이 병원(CHOP)에 있는 6개의 다른 곳에서 환자 등록을 받을 것이다.
지난 1월 첫 환자가 등록한 필라델피아 어린이 병원의 공동 선임연구원인 리차드 아플렌크 박사는 "1차 시험을 위해 장소가 복수이면 연구원들과 환자 모두에게 좋을 것"이라고 말했다.
아플렌크 박사는 "이러한 조사 요법에 대한 접근을 정말로 확대할 것이며, 연구소는 미국의 동서 양 해안 지방과 중부지방에 있다."고 말했다.
웰치 박사는 연구원들이 고형 암을 포함한 다른 암에 대한 선택지로 CAR T-세포요법을 확대하고자 할 때 이들의 성공에 대한 장벽을 낮추는 것이 매우 중요할 것이라고 말했다.
그는 “그것이 우리가 지원하려는 아이디어이며, 우리는 이러한 치료법들을 초기 임상시험에 더 많이 도입하도록 도와줌으로써 혁신적인 개념과 아이디어의 개발로 인한 위험의 일부를 제거하고 있다.”고 말했다.
혈액 채취부터 공학적으로 조작한 세포 치료까지
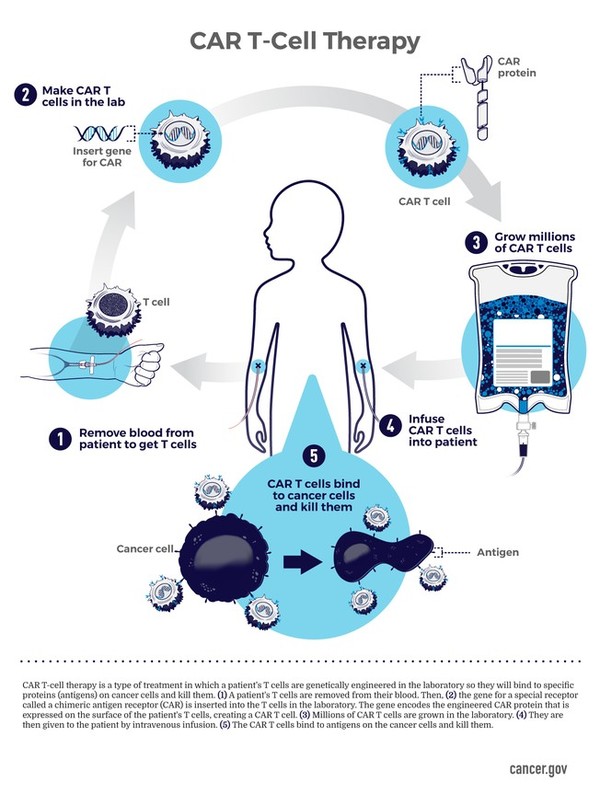
간단히 말해서 CAR T세포 요법의 제조는 이와 같이 작용한다.
첫째, 환자 자신의 혈액을 채취하여 그 혈액에서 나온 백혈구를 분리하고, 그 나머지 적혈구와 혈장을 환자에게 돌려주는 과정을 백혈구 성분 채집술(백혈구 분반술)이라고 한다.
일단 수집된 백혈구가 확보되면, 연구 단체들은 다른 백혈구로부터 특정 T세포를 분리하기 위해 다양한 방법을 사용한다. 그리고 무장 해제된 바이러스는 단백질의 표면에 있는 키메릭 항원 수용체(CAR)와 세포 내부에 존재하는 공동 자극 분자를 생산하라는 T세포에 유전자 지시를 전달하는 데 사용된다.(T세포가 계속 활동하게 하는 신호를 전달함으로써, CAR T세포가 살아남도록 돕고 환자에게 다시 투입되면 성장한다.)
다음으로, 이 작은 묶음의 CAR T 세포는 수백만 개로 증식될 때까지 유도되며, 이 과정은 T 세포의 적절한 "투여량"에 도달할 수 있을 만큼 충분히 숫자가 증가하도록 세심하게 모니터를 항다.
제조 과정의 마지막 단계는 CAR T 세포의 순수성과 품질을 보장하기 위해 몇 가지 중요한 관리과정이 필요하며, 이 때 CAR T 세포는 환자에게 다시 주입될 준비가 된다.
CAR-T 세포의 제조
1. T세포의 농축과 활성화
2. 렌티바이러스의 CAR로 전도
3. CAR-발현 T세포의 확장
4. 최종 세포 제품의 분리
※CAR T세포요법에서, 환자들이 백혈구성분채집술(백혈구분반술)을 받은 후, 그들의 T세포는 정맥주사를 통해 그들이 받은 수억 개의 유전자 변형 T세포를 생산하는 복잡한 과정을 겪게 된다.
CD33 CAR T세포 시험 연구의 공동 리더인 국립암연구소 암 연구 센터의 니랄리 샤 박사는 현재 소수의 연구실만이 CAR T 세포를 만들 수 있다고 말했다.
"어떤 실험실에서나 세포를 제조해서 환자에게 줄 수는 없다. 인프라와 지원, 지식을 갖춰야 이 일을 잘할 수 있다."고 미국 메릴랜드 주 베데스다의 국립보건원 임상센터에서 혈액 암을 앓고 있는 어린이들을 대상으로 여러 차례 CAR T세포 치료법 실험을 주도해 온 샤 박사가 말했다.
메릴랜드 주 프레데릭에 있는 국립암연구실험실의 생물 의약품 개발 프로그램(BDP)이라는 기존 시성을 통해, 생물 제품을 제조하기 위해 국립암연구소가 CAR T세포 연구를 가속화할 수 있는 중요한 필요를 충족시킬 수 있는 기회가 있었다고 웰치 박사는 말했다.
그는 "생물 의학품 개발프로그램(BDP)은 초기 실험을 지원하기 위해 바이러스와 항체, 단백질, 백신 제조 경험을 갖고 있고, 품질 제조 공정에 대한 경험이 있다."고 말했다.
그러나 이 프로그램에 없는 것은 CAR T 세포 제조 경험이었다.
신속한 작업에 중요한 협업
국립암연구소의 지도부의 제조 노력을 지원하겠다는 약속을 받아, 다음 단계는 지원을 할 첫 번째 시험을 식별하고 제조 공정을 확립하는 것이었다.
국립암연구소에서 CAR T-세포요법을 개발하고 테스트하는 데 있어 국내 최고의 전문가들을 확보하고 있는 것이 첫 단계에 도움이 되었다. 샤 박사와 국립암연구소의 POB(소아 종양학과)의 동료들은 이미 급성 골수성 백혈병 소아 환자들을 위한 시험을 위해 움직이고 있는 CD33 CAR T 세포에 대해 연구하고 있었다. 이 특정한 CAR은 이전에는 소아종양학과(POB)에서 일했고 지금은 콜로라도 대학교 의과대학에 재직 중인 테리 프라이 박사에 의해 개발되었다.
샤 박사는 "CD33의 개념이 처음 개발되었을 때, 이전에는 멀티 센터 실험을 계획할 수 있는 기반시설이 없었기 때문에 우리는 모두 단일 센터의 1상 실험이 될 것이라고 생각하고 있었다."고 말했다.
그러나 연구 지역사회에서는 샤와 아플렌크 박사를 좋아한다. 왜냐하면 혈액 암에 걸린 어린이들을 위한 줄기세포 이식을 포함한 치료법을 개발하고 실험하는 데 주력하고 있는 그들의 연구가 매우 협력적이기 때문이라고 그녀는 말했다. 그리고 국립암연구소 제조 계획이 온라인에 올라오면서, 그녀는 "이제 멀티 센터 시험에 대해 생각할 수 있는 메커니즘(기전)이 생겼다"고 덧붙였다.
그 연구 지역사회에는 이 실험의 주요 후원자로 승선했던 국제혈액 이식 연구 센터와 그 전반적인 행위(예: 세포의 운송을 감독·조정, 환자안전 감시)를 관리하는 국립골수 기증 프로그램이 포함된다.
다음은 제조 공정을 해결할 때였다. 그 위치는 이미 밝혀져 있었다. 즉 박테리아와 단백질과 같은 생물학적 원천으로부터 약물과 치료법을 제조하는 생물의약품 개발 프로그램이었다.
그 후 국립암연구소 팀은 제조 전문성을 위해 상급기관인 국립보건원으로 눈을 돌렸다. 이들이 상담한 전문가로는 국립보건원 내 연구자들을 위한 CAR T 세포 등 세포 치료법을 개발하고 제조한 경험이 풍부한 국립보건원의 세포공학센터의 데이비드 스트론체크 박사와 스티브 하이필 박사 등이 포함됐다.
웰치 박사는 "그들의 전문지식과 경험은 매우 소중했다"고 말했다. 이러한 지침과 피드백으로 무장한 국립암연구소 팀은 상용화된 비교적 새로운 시스템을 CAR T 셀 제조에 사용하기로 결정했다.
국립암연구소 암 치료 및 진단 부서(DCTD)의 제이슨 요반디치 박사는 "영재/신동"이라고 불리는 이 시스템은 환자로부터 수집된 세포를 시스템에 넣으면 나머지를 처리해 2주 이내에 완성된 CAR T세포 제품을 생산한다는 것을 의미한다고 설명했다.
이때까지 대부분의 실험실과 FDA가 승인한 두 가지 CAR T세포 치료제를 제조하는 회사들은 최종 제품을 생산하기 위해 더 많은 수동 조작이 필요한 "개방형" 시스템을 사용해 왔다. 요반디치 박사는 폐쇄적인 시스템을 가지고는 "환자 세포가 들어가는 것만이 유일한 변수"라고 말했다.
현재 국립암연구소는 2개의 ‘영재/신동' 장비를 보유하고 있으며, 3번째 장비를 추가할 계획이다. "이 계획이 어떻게 진행되느냐에 따라 더 많은 것이 추가될 수 있다"고 그는 말했다.
다른 모델
CAR T-cell 요법의 수많은 임상실험이 필라델피아 어린이 병원에서 행해졌다. 아플랜크 박사는 치료법이 사내에서 제조되지 않을 때 실험을 수행하는 데 예상 외로 차이가 있다고 말했다. 그러나 다중 센터 시험의 경우 단일 제조사가 이상적인 선택인 것 같다.
그는 "국립암연구소가 세포 제조를 하지 않았다면 이 다중센터 시험을 하는 것은 매우 어려운 일일 것"이라고 말했다.
아플렌크 박사는 CD33 CAR T 세포를 한 곳에서 만드는 데 아무런 문제가 없을 것으로 예상한다고 말했다. CAR T세포요법이 단일 기관에서 사내에서 생산될 때도 항상 처리해야 할 실행계획이 있다. 예를 들어, 제조 시간은 그 센터의 현재의 대기 수량에 의해 작동되며 그 대기 수량은 환자의 수와 제조 처리량에 달려있다."고 그는 말했다.
그리고 CAR T세포 치료법의 제조가 더욱 자동화되어 이러한 치료법과 관련된 연구에 참여하는 실험실의 수가 증가할 것으로 예상됨에도 불구하고, 중앙 집중화된 접근방식은 새로운 치료법에 대한 인간의 임상연구에 중요한 역할을 할 수 있다고 샤 박사는 지적했다. "이런 모델은 정말 크게 기대할만 한 것 같다"고 그녀는 말했다.
웰치 박사는 제조 세부계획이 아직 초기 단계라고 강조했으며 어떻게 진행되는지 보는 데 시간이 걸릴 것이라고 말했다. 그는 "우리는 여전히 아기 걸음마를 하고 있다"고 말했다.
그렇더라도 여기까지 오려면 많은 작업과 협업이 필요했다. 그는 "이런 걸 합치려면 그렇게 해야 한다"고 말했다. 이 협력은 "우리가 이룬 진전에 대단히 중요했다"고 말했다.
2020년 4월 23일 : 국립암연구소 제공
NCI Initiative Aims to Boost CAR T-Cell Therapy Clinical Trials
April 23, 2020, by NCI Staff
In 2010, an NCI research team published the first study of a new form of cancer treatment called CAR T-cell therapy, reporting on a single patient with advanced lymphoma whose disease, they recounted, “underwent a dramatic regression” following the treatment. The next year, researchers from the University of Pennsylvania reported a similar result using CAR T-cell therapy to treat a patient with an advanced form of leukemia.
Within 7 years, the Food and Drug Administration (FDA) approved the first two CAR T-cell therapies, and with a third approval expected sometime this year, research groups around the world are rapidly developing new CAR T-cell therapies.
These cancer treatments have captured public attention, and researchers’ imaginations, like few others. In part, that’s because of the remarkable way they can eliminate cancer in some people with advanced blood cancers. It’s also because of where they come from: a patient’s own blood. Components of that blood are then used to create the treatment.
Transforming those components into the therapy that is eventually returned to the patient requires a highly complex manufacturing process. And that’s part of what sets CAR T-cell therapy apart from most other cancer treatments, explained Anthony Welch, Ph.D., a project officer in NCI’s Division of Cancer Treatment and Diagnosis (DCTD).
“With CAR T cells, the process is the product,” Dr. Welch said. That process is also expensive, complicated, and highly regulated.
That’s part of what makes conducting human clinical trials testing these individualized CAR T-cell therapies more challenging than those involving “off-the-shelf” drugs that are manufactured in massive batches. Few laboratories and centers have the capability to make CAR T cells, which has limited the ability to test them more broadly.
To help address these challenges, more than a year ago, DCTD and NCI leaders turned to their experts at the Frederick National Lab for Cancer Research (FNLCR) and tasked them with developing the capability to produce cellular therapies like CAR T cells for cancer. Specifically, the goal was to accelerate the ability to test these therapies in clinical trials to be conducted at multiple hospital sites.
The initial clinical trial supported by this effort will be the first trial to test a CAR T-cell therapy designed to target a protein on cancer cells called CD33 in children and young adults with advanced forms of acute myeloid leukemia (AML). It will ultimately enroll patients at six different sites, starting at the NIH Clinical Center in Bethesda, MD, and the Children’s Hospital of Philadelphia (CHOP).
Having multiple sites for the first trial will be good for both the investigators and the patients, said the trial’s co-lead investigator, Richard Aplenc, M.D., of CHOP, where the first patient on the trial was enrolled in January.
“It will really expand access to this investigational therapy,” Dr. Aplenc continued. “We have sites on both coasts and in the middle of the country.”
And as researchers look to expand CAR T-cell therapy as an option for other cancers, including solid tumors, Dr. Welch said, lowering the barriers to their success will be critical.
“That’s the idea we’re trying to support,” he said. “We’re taking some of the risk out of [developing] innovative concepts and ideas by helping to bring more of these therapies into early clinical trials.”
From a Blood Collection to an Engineered Cell Therapy
In a nutshell, the manufacturing of a CAR T-cell therapy works like this.
First, a patient’s own blood is collected and the white blood cells from that collection are separated out, with the remaining red blood cells and plasma returned to the patient, a process known as leukapheresis.
Once the collected white blood cells are in hand, research groups use various methods to isolate specific T cells from the other white blood cells. Then, a disarmed virus is used to deliver genetic instructions to the T cells telling them to produce the chimeric antigen receptor (CAR), which ends up on their surfaces, and co-stimulatory molecules, which reside inside the cell. (By delivering signals that keep the T cells active, the co-stimulatory molecules help the CAR T cells to survive and grow once introduced back into the patient.)
Next, this small batch of CAR T cells is induced to multiply until they number in the millions, a process that is carefully monitored to ensure that they grow enough in number to achieve the appropriate “dose” of T cells.
The final step in the manufacturing journey requires some important housekeeping to ensure the purity and quality of the CAR T cells, at which point they are ready to be infused back into the patient.
Manufacture of CAR-T cells
& activation of T cells
with lentiviral CAR construct
of CAR-expressing T cells
of final cell product
In CAR T-cell therapy, after patients undergo leukapheresis, their T cells are subject to a complex process that produces hundreds of millions of genetically modified T cells that they then receive via intravenous infusion.
At the moment, only a small group of research labs have the ability to make CAR T cells, said Nirali Shah, M.D., of NCI’s Center for Cancer Research, the co-lead investigator on the CD33 CAR T-cell trial.
“You can’t just manufacture cells in any lab and give them to patients,” said Dr. Shah, who has led several trials of CAR T-cell therapies in children with blood cancers at the NIH Clinical Center in Bethesda, MD. “You need to have the infrastructure and the support and the knowledge to be able to do this well.”
With an existing facility, the Biopharmaceutical Development Program (BDP) at the FNLCR in Frederick, MD, for manufacturing biological products, Dr. Welch said, there was an opportunity for NCI to help meet a critical need to help accelerate CAR T-cell research.
“The BDP has experience manufacturing viruses, antibodies, proteins, and vaccines to support early trials,” he added. “It has experience with quality manufacturing processes.”
What the program didn’t have, however, was experience manufacturing CAR T cells.
Collaborations Critical to Quick Action
With a commitment from NCI leadership to back the manufacturing effort, the next steps were to identify the first trial to be supported and establish the manufacturing process.
Having some of the country’s leading experts in developing and testing CAR T-cell therapies at NCI helped with the first step. Dr. Shah and her colleagues in NCI’s Pediatric Oncology Branch (POB) were already working on a CD33 CAR T cell that they were moving toward a trial for children with AML. This specific CAR was initially developed by Terry Fry, M.D., formerly of the POB and now at the University of Colorado School of Medicine.
“When the CD33 concept was first developed, we were all thinking it would be a single-center phase 1 trial, because we previously did not have the infrastructure to plan for a multicenter trial,” Dr. Shah said.
But the community of researchers like Drs. Shah and Aplenc, whose work focuses on developing and testing treatments, including stem cell transplants, for children with blood cancers is highly collaborative, she said. And with the NCI manufacturing initiative coming online, she added, “there was now a mechanism to think about a multicenter trial.”
That research community includes the Center for International Blood and Marrow Transplant Research, which came on board as the trial’s primary sponsor, and the National Marrow Donor Program, which will manage its overall conduct (e.g., overseeing and coordinating the shipping of cells, monitoring patient safety).
Next, it was time to nail down the manufacturing process. The location had already been identified: the BDP, which manufactures drugs and therapies from biological sources, such as bacteria and proteins, for research studies.
The NCI team then turned to NIH for manufacturing expertise. The experts they consulted included David Stroncek, M.D., and Steve Highfill, Ph.D., of NIH’s Center for Cellular Engineering, which has extensive experience developing and manufacturing cell therapies, including CAR T cells, for investigators within NIH.
“Their expertise and experience was invaluable,” Dr. Welch said.
Armed with this guidance and feedback, the NCI team decided to use a relatively new, commercially available system for manufacturing CAR T cells.
The system, called Prodigy, is “closed,” meaning that once the collected cells from the patient are put into the system, it takes care of the rest, producing a completed CAR T-cell product within 2 weeks, explained Jason Yovandich, Ph.D., also of DCTD.
Up to this point, most laboratories and the companies that manufacture the two FDA-approved CAR T-cell therapies have used “open” systems, which require more manual manipulation to produce a final product. With a closed system, Dr. Yovandich said, “the only variable to account for is the patient cells going in.”
Currently, NCI has two Prodigy systems, with plans to add a third. Depending on how this initiative progresses, more could be added, he said.
A Different Model
Numerous clinical trials of CAR T-cell therapies have been conducted at CHOP. Dr. Aplenc said that, not unexpectedly, there are differences conducting a trial when the treatment is not being manufactured in house. But for a multicenter trial, a single manufacturer seems to be the ideal choice.
“If NCI was not doing the cell manufacturing, it would be extremely challenging to do this [multicenter trial],” he said.
Dr. Aplenc said he doesn’t expect any issues with having the CD33 CAR T cells made at a single location. Even when a CAR T-cell therapy is produced in house at a single institution, there are always logistics to deal with. For example, the manufacturing time “is driven by the current queue at that center, which can be driven by patient volume and manufacturing throughput,” he said.
And even as the manufacturing of CAR T-cell therapies becomes more automated, which is expected to increase the number of labs involved in research involving these therapies, a centralized approach can play an important role in human clinical studies of new treatments, Dr. Shah noted. “I think a model like this has so much promise,” she said.
Dr. Welch emphasized that it’s still early days for the manufacturing initiative and that it will take time to see how it plays out. “We’re still taking baby steps,” he said.
Even so, it’s taken a lot of work and collaboration to get this far. “That’s what it takes to put something like this together,” he said. The collaboration “has been tremendous and critical to the progress we have made.”
이 글은 2020년 5월 작성 시점의 정보입니다. 치료 기준·급여 정보는 바뀌었을 수 있으니, 진료와 치료 결정은 반드시 담당 의료진과 상의하세요.



